
Every vendor in post-acute care claims to reduce rehospitalizations. Far fewer will show you how they measure it. Fewer still will let you see the number for your own organization, updated as the data comes in, using a methodology you can inspect.
At Saiva, tracking unplanned return-to-hospital (RTH) rates is not a sales exercise, it is a standard part of how we work. From the day a SNF group is onboarded , we track their RTH per 1,000 patient days against their own pre-Saiva baseline, using the same methodology across every partner. That means when we tell an SNF group their rate has moved, we can show them exactly how, over what period, and with what statistical confidence.
Below is what that looks like across the eight SNF groups.
The measurement approach
For each SNF Group, we compare daily unplanned RTH rates per 1,000 patient days before and after their Saiva go-live date. The pre-Saiva window is the organization’s own historical baseline. The post-Saiva window is everything after go-live. Each daily rate is calculated the same way, using the same source data, so the comparison is clean.
Two things matter about this approach.
First, every SNF group is measured against itself. We are not comparing one SNF to another, and we are not comparing
SNF groups to a national benchmark that may or may not reflect their patient mix. Your baseline is your baseline. That is the number the change is measured against.
Second, the measurement is continuous. It is not a quarterly snapshot. It is a daily view, which means the trajectory is visible in real time, not only in retrospect after a reporting cycle closes.
What the tracking has shown
Across these eight SNF groups, ranging from a three-facility group to a network of fifteen, every single one saw a reduction in unplanned RTH rates after implementing Saiva.
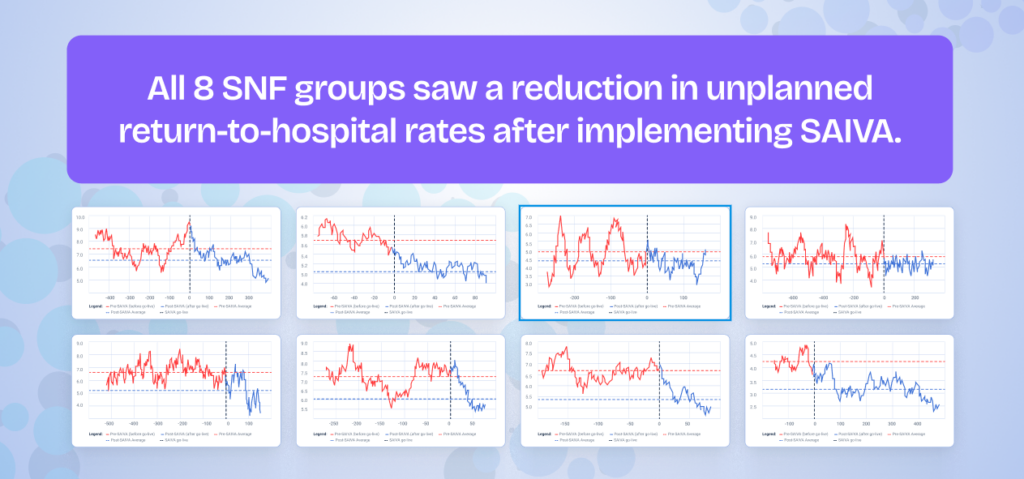
The reductions were not identical. Some SNF group moved from 6.8 to 5.3 per 1,000 patient days. Others went from 4.2 to 3.1, or from 5.7 to 5.0. The absolute change ranged from about half a point to nearly a point and a half. In percentage terms, most SNF groups cut their unplanned transfer rate by somewhere between 10 and 25 percent.
Consistency across a mixed set of SNF groups matters more here than any single number. Facility mix varied. Payer mix varied. Baseline rates varied. Clinical leadership styles varied. What did not vary was the direction of the change.
A few observations worth naming.
The change was durable. These are not week-one improvements that faded by month three. In the longer time series, the post-Saiva rate stays below the pre-Saiva average for hundreds of days after Saiva’s implementation. That is what a real workflow shift looks like when it holds.
The effect showed up regardless of where a SNF group was starting from. The lowest-baseline SNF, already at 4.2 per 1,000 patient days, still saw meaningful reduction. That counters the assumption that early intervention tools only help facilities that are underperforming. SNF groups already doing well got better too.
Why this kind of tracking should be standard
Rehospitalization reduction is one of the most consequential metrics in post-acute care. CMS penalties, PDPM performance, payer contract terms, and star ratings all connect back to it. And yet most SNF operators run months at a time without a clear view of whether the initiatives they have invested in are actually moving the number.
That gap between doing the work and seeing the result is what makes clinical change so hard to sustain. Teams launch protocols and wait for the quarterly report to tell them if the protocol worked. By the time the answer comes, the team has moved on to the next initiative, the staffing picture has changed, and the specific decisions that drove the outcome are hard to reconstruct.
Continuous tracking closes that gap. When RTH is measured daily against a stable baseline, the impact of a change becomes visible while it is still happening. That visibility is what makes it possible to reinforce what is working, adjust what is not, and hold the improvement in place.
This is not a special report we build for a subset of customers. It is the standard tracking every Saiva’s SNF group has access to.
For post-acute leaders
The question worth asking any Predictive Analytics tool is not “will you reduce our rehospitalizations.” Every vendor will say yes. The question is “how will they prove it?”
Continuous RTH tracking against a SNF group’s own baseline is the answer we can point to. It is a shared source of truth between our team and yours, one that stays live for the full length of the engagement.
The rate is movable. The data across eight SNF groups shows that. What makes it stay moving is the ability to see the change as it happens, and to know, with confidence, that the work is working.